

The short version
Thank you to each and every one of you who sent up a prayer, mailed a card, or passed along good wishes while I’ve been dealing with some health challenges.
Yes, I am “on the mend.”
No, it won’t be a fast process.
I can’t even estimate what lies ahead because new problems have had an annoying habit of cropping up just when I think I know the plan. But the good news—the very good news—is that I am making progress.
Please know how much I appreciate every prayer, card, message, and good thought you’ve sent my way.

The long version
Grab a cup of tea or coffee and get comfy.
My dad died at 47 after multiple heart attacks and open-heart surgery. My grandfather also died from heart problems. My mother’s health history is a mystery because she was adopted.
So, given this and our advancing ages, my two sisters and I seemed like excellent candidates when our doctors urged us to get CAC tests.
CAC stands for coronary artery calcium. It’s a quick, noninvasive CT scan that looks for calcium in the coronary arteries—the vessels that supply blood to your heart. Calcium levels indicate plaque, and the resulting score can help doctors estimate a person’s risk of coronary heart disease and decide whether preventive treatment may be appropriate.
I had the test.
A few days later, my primary care provider called.
She encouraged me to see a cardiologist “sooner rather than later.”
Now, there’s a phrase you don’t want to hear from your doctor.
I made the first available appointment.
It was several months away.
And then, because I felt fine and had a life to live, I did what human beings are remarkably good at doing.
I put it out of my mind.
Months passed.
When I finally met my new cardiologist, he reminded me of my own son: youthful face, sparse beard, no-nonsense manner.
“First, we need to do a heart catheterization to get a better look at what’s going on,” he told me. Depending on what they found, they might be able to open a blockage and place a stent.
And if they couldn’t?
“The next step would be open-heart surgery.”
Open-heart surgery?
Surely I had misheard him.
I busted out laughing.
“You have to be kidding…right?”
He wasn’t kidding.
Then, almost as an aside, he added another surprise.
“By the way, you have a heart murmur. You knew that, right?”
No.
I did not.
At this point, my brain had more incoming information than available processing power.
And for some reason, my mind took a stroll down memory lane.
I was a teenager when Dr. Christiaan Barnard, a South African surgeon, astonished the world by performing the first human-to-human heart transplant in 1967.

.
For years, I had remembered Barnard as the man who ushered in the age of open-heart surgery.
I was wrong.
Surgeons had already been opening and repairing human hearts for more than a decade. In 1953, Dr. John Gibbon successfully used a heart-lung machine during open-heart surgery, temporarily doing the work of the patient’s heart and lungs while he repaired the heart itself. Other pioneering surgeons quickly advanced the field.
Barnard did something even more audacious.
He replaced the heart.
Think about that for a moment.
He removed the failing heart from a living human being, replaced it with another person's heart, and connected it to the recipient’s circulation—and that relocated heart went on to beat for 18 days.
No wonder the world was astonished.
And now, nearly six decades later, this young doctor with the sparse beard was sitting across from me, calmly discussing the possibility of opening my chest.
Suddenly, medical history felt a lot less historical.
Needless to say, I scheduled the heart catheterization.
The receptionist assured me it was a routine procedure. In fact, she told me, her son had undergone it five times.
I was tempted to ask, “Because they couldn’t get it right the first time?”
But I behaved myself.
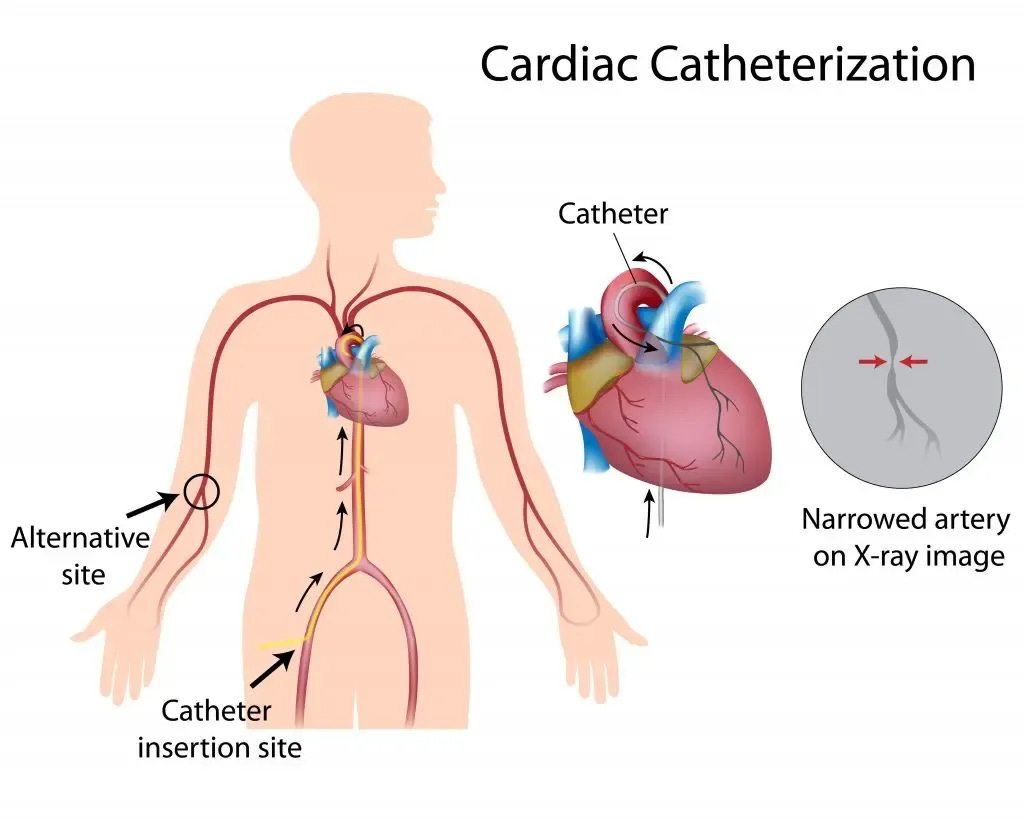
The catheterization would allow the cardiologist to guide a thin tube through an artery—often from the wrist or groin—toward the heart. Contrast dye and X-ray imaging would show the coronary arteries and reveal exactly where blood flow was being restricted.
Best-case scenario?
They’d find a blockage they could treat right then, perhaps with a balloon and stent to hold the artery open.
Bada-bing, bada-boom. Fix the plumbing, close her up, everybody goes home.
Uh…
Not so fast.
When it was over, I woke up to news I had never imagined hearing.
I needed open-heart surgery.
The catheterization had revealed a dangerously located coronary blockage—the kind of anatomy doctors take very seriously because an acute obstruction there can jeopardize a large portion of the heart muscle.
Suddenly, this wasn’t an abstract discussion about cholesterol scores, family history, or something that might happen someday.
This was my heart.
And here is the part that has stayed with me.
I thought about all the times I’d traveled alone throughout Europe.
All those peaceful days I’d spent writing in an empty house.
All those solitary walks along the beach that I treasure.
I had felt perfectly comfortable being alone because I had no idea anything was seriously wrong.
That may be the most unsettling lesson my heart has taught me so far:
Sometimes the absence of symptoms is not the same thing as the absence of disease.
And I was about to learn how this disease had been hiding inside me.
Part II: Open-heart surgery.
Know anyone who has had it? Anyone who has had a heart catheterization?
My dad had open heart surgery in 1973 or 74. As the story goes, the guy that ran the heart pump was the guy that ran it for Bernard when he did the first transplant. Dad didn’t think he looked like he had enough sense to come in out of the rain! 🤦♀️🤷♀️. He had 90% blockage in 2 arteries. He was in his 50’s when he had the surgery. He lived to a few days short of 94. He also had diabetes & COPD. He lived a very full life. I wish you the same outcome! 💜💜
My husband had double bi-pass and an aortic valve replaced 3 yrs ago. He was 67 and has done great. Thoughts and prayers your recovery will go smoothly.